Broken Incentives: How Flawed Tax Policies Fuel the Antimicrobial Resistance Crisis and Fiscal Waste
LONDON — In an era defined by overlapping global emergencies, policymakers and financial experts frequently diagnose systemic failures in isolation. Yet, the root causes of our most pressing public health and fiscal dilemmas are often deeply intertwined.
At a time when antimicrobial resistance (AMR) poses an existential threat to modern medicine and global economic stability, prevailing tax structures actively incentivize corporate financial engineering over life-saving pharmaceutical innovation. Strikingly, this same disconnect—where rewards are detached from genuine societal value—lies at the heart of ballooning, out-of-control public spending.
Recent high-level discussions in London and international financial circles have reinforced a growing suspicion among economists: too many institutional experts operate within rigid intellectual silos, failing to connect the foundational dots between macroeconomic tax policy, corporate behavior, and the impending failure of our global healthcare safety net.
1. Main Facts: The Convergence of Economic Inefficiency and Public Health Peril
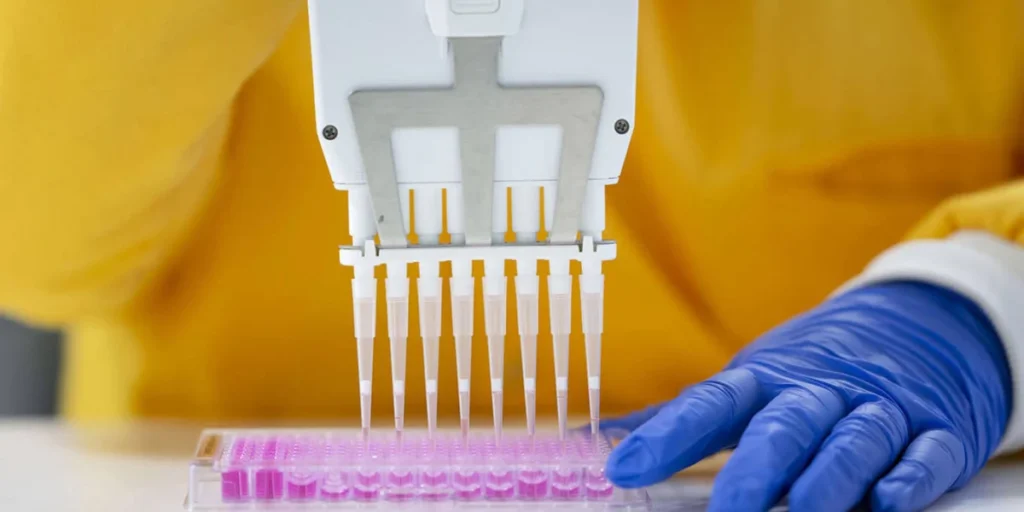
To understand the modern crisis of antimicrobial resistance, one must first look at the economics of pharmaceutical R&D. Antibiotics operate under a unique and paradoxical market failure. Unlike treatments for chronic conditions—such as cancer, diabetes, or cardiovascular disease—which patients take for years or lifetimes, effective antibiotics cure an infection in a matter of days. Furthermore, to prevent the emergence of superbugs, new antibiotics must be strictly conserved rather than mass-marketed.
For pharmaceutical companies, this means the commercial return on investment (ROI) for a breakthrough antibiotic is abysmally low. Consequently, major drug developers have largely abandoned the antimicrobial space, redirecting capital toward more lucrative therapeutic areas or corporate stock buybacks.
At the same time, global tax codes exacerbate this market failure. Rather than rewarding long-term capital expenditure (CapEx) in high-risk, high-reward sectors like infectious disease research, modern tax regimes often favor short-term financial engineering. Debt-financed mergers and acquisitions, share buybacks, and sophisticated tax arbitrage offer superior returns for shareholders, driving capital away from socially vital R&D.
This perverse alignment of incentives is not confined to the private sector. On the macroeconomic front, public spending frameworks often mirror corporate myopia. Governments frequently allocate budgets based on legacy spending patterns and political expediency rather than rigorous cost-benefit analyses, mirroring the way capital markets misallocate resources away from public health infrastructure.
2. Chronology: How We Arrived at the Crossroads of AMR and Fiscal Strain
The roots of the modern antimicrobial dilemma stretch back decades, forming a timeline defined by scientific triumph followed by structural neglect.
- The Golden Age of Antibiotics (1940s–1960s): Following the widespread adoption of penicillin, researchers rapidly discovered and commercialized numerous classes of antibiotics. During this era, pharmaceutical companies viewed antibiotic development as both scientifically feasible and commercially viable.
- The R&D Drought (1980s–2000s): As "low-hanging fruit" discoveries dwindled, the cost and scientific complexity of discovering new antibiotic classes skyrocketed. Simultaneously, the commercial return plummeted as regulatory hurdles increased and new drugs were restricted to reserve status to prevent resistance. Major pharmaceutical conglomerates began downsizing or entirely shuttering their anti-infective divisions.
- The Rise of Shareholder Primacy (2000s–2010s): Global tax reforms and monetary policies—particularly prolonged low interest rates—triggered a boom in corporate financial engineering. Companies increasingly utilized cheap debt and tax-advantaged structures to fund share buybacks rather than long-term research, hollowing out industrial innovation capacity.
- The Post-Pandemic Fiscal Reckoning (2020–2025): The COVID-19 pandemic laid bare the fragility of global health security and triggered massive emergency public spending. As governments accumulated historic levels of sovereign debt, the inefficiency of public expenditure came under intense scrutiny. Yet, despite the lessons of the pandemic, structural investments in AMR countermeasures remained severely underfunded.
- The Present Day (2026): Public health bodies and economic institutions increasingly sound the alarm that the post-antibiotic era is no longer a distant theoretical threat. Without fundamental reforms to tax policy and public financing models, routine surgeries, cancer treatments, and minor injuries risk becoming fatal once again.
3. Supporting Data: The Numbers Behind the Crisis
A rigorous examination of the data reveals the profound misalignment between capital allocation and societal needs.
- The R&D Gap: According to global health metrics, while the global burden of drug-resistant infections continues to climb—responsible for millions of deaths annually—fewer than a dozen novel systemic antibiotics are currently in late-stage clinical trials.
- Financial Engineering vs. Investment: Over the past decade, major publicly traded pharmaceutical and healthcare firms have routinely channeled over 50% to 70% of their free cash flow into share buybacks and dividends, compared to a shrinking fraction allocated to high-risk anti-infective research.
- The Economic Burden of AMR: The World Bank estimates that unchecked antimicrobial resistance could result in a drop in global GDP comparable to the 2008 financial crisis, forcing up to 24 million people into extreme poverty by 2030, predominantly in developing nations.
- Public Spending Inefficiencies: Independent fiscal watchdogs note that structural waste in public spending—driven by legacy administrative models and a lack of outcome-based budgeting—accounts for a significant percentage of national deficits in advanced economies, funds that could otherwise be redirected toward strategic health security reserves.
4. Official Responses and Policy Debates
Governments, multilateral institutions, and central banks are facing mounting pressure to dismantle institutional silos and reform the frameworks governing both tax codes and public budgets.
The Push for "Pull" Incentives
Health economists and pharmaceutical advocates have long championed the introduction of market "pull" mechanisms—such as subscription-style subscription models (pioneered in part by the UK’s NHS antimicrobials pilot)—which decouple a drug’s revenue from the volume sold. By guaranteeing a fixed return for a successful, novel antibiotic, these models aim to restore commercial viability to the sector. However, scaling these pilot programs globally remains an uphill political battle.
Tax Reform Proposals
Progressive economic reformers are calling for a fundamental overhaul of corporate tax architecture. Proposals include introducing preferential tax credits for R&D expenditures directed toward World Health Organization (WHO)-designated priority pathogens, alongside punitive tax treatments for excessive share buybacks and unproductive financial engineering.
Fiscal Discipline and Strategic Spending
On the macroeconomic side, fiscal authorities are under pressure to adopt "smart spending" frameworks. International financial institutions are urging governments to move away from incremental budgeting and toward zero-based budgeting, ensuring that public funds actively crowd in private investment for critical infrastructure, green technology, and health security rather than subsidizing economic rent-seeking.
5. Implications: The Stakes for the Global Economy and Public Health
The convergence of antimicrobial resistance and flawed public finance represents a critical stress test for modern capitalism and governance.
If tax policies continue to reward short-term financial maneuvering over foundational scientific research, the consequences will extend far beyond balance sheets. A failure to incentivize antibiotic development guarantees the arrival of a post-antibiotic era, rendering modern medicine paralyzed in the face of routine bacterial infections. The human toll would be catastrophic, accompanied by a simultaneous collapse of labor productivity and healthcare systems worldwide.
Simultaneously, unaddressed inefficiencies in public spending threaten sovereign debt sustainability. When governments fail to align their fiscal outlays with long-term societal resilience, they forfeit the fiscal space required to combat systemic shocks—whether biological, environmental, or economic.
Breaking the Silos
Ultimately, the path forward demands an intellectual and institutional paradigm shift. Policymakers, tax authorities, public health officials, and corporate leaders can no longer operate in isolation. Connecting the dots between how we tax corporations and how we safeguard human health is no longer merely an academic exercise; it is an urgent economic and moral imperative for the 21st century.